“Whenever I walk it feel as if my sole has become thick, senseles and sometimes it quite weak to hold my legs firmly on the ground. It makes me insecure and afraid of falling”
A Case Study.
A lady of around 52 years of age came to us with complain of numbness on both the sole of the foot. she also complained of slight difficulty in moving legs during the stance phase of the gait cycle.
She described that “Whenever I walk it feel as if my sole has become thick and sometimes it quite weak to hold my legs firmly on the ground. It makes me insecure and afraid of falling” told the lady who complains of the problem since past 8 years.
They have many history of treatment within the span of eight years without any benefit. Recently they consulted neurologist and an MRI scan and X-ray was suggested for Low back. The report revealed a low to mild central disc bulge at L4-L5 level and based on this report a spinal extension exercises were prescribed.
Surprisingly, spinal extension exercises also did not prove to be beneficial. The MRI report says it is an L4–L5 disc bulge but still the spinal extension exercise did not help, why?
By the time when I discharged her after 17 sittings she had reported around 70%–80% of improvement. If you read further you will understand that being the tricky case, still its treatment is so simple.
What we found?
When she came to us she seemed to be exhaust, after all nothing improved her ailment. But she was cooperative. I checked through all her previous treatment records and her diagnostic report.
As I have already mentioned that MRI report suggests low to mild L4-L5 disc bulge, this prompted us to direct our assessment towards this. But, none of her complains and our assessment supported it. Here is the set of questions i asked her as a part of my assessment process we carried out.
Q 1: how did you start your problem?
Ans- It all started eight years back spontaneously and become worse with time.
Q 2: do you have pain in your back now?
Ans: No I don’t.
Q3: Do you before ever had any serious back pain?
Ans: No.
Q4: That means you never had pain in your low back and back of thigh and leg?
Ans: Yes, I never had any such complain.
Q5: Do you feel any kind of tingling sensation on the back of the leg?
Ans: No.
Q6: When do you feel numbness on your sole of the foot?
Ans: I feel it all the time but I appreciate it more when walking, along with slight weakness on legs.
Our Physiotherapy assessment.
Movement: All the lumbar movement (forward bending, side bending, extension) is pain-free with no other symptoms.
Central PA (Posterior to Anterior mobilization) at L4-L5 – No Abnormality Detected.
Treatment
Our assessments lead us to nowhere. MRI report says she has low to mild disc bulge but there is no symptoms of it.
Still, we planned the treatment in the line of the disc bulge.
We advised for:
- Intermittent Lumbar Traction.
- TENS
- Spinal extension exercises.
After five treatment session, we were still puzzled as there was no sign of improvement.
But ultimately we got the result.
Do you think our previous treatment plan worked?
No!
This prompted us to look at the case from the different angle. This time, we planned to treat her symptomatically.
She has symptoms of numbness on the sole of the foot (Please note that she is not a Diabetic and all other neurological condition is ruled out), so we decided to go for Galvanic stimulation.
We gave 15-20 minutes session of galvanic stimulation on the back of the leg. On the third session, she indicated the sign of improvement.
By the end of the 17th visit, she reported about 70% to 80% of improvement.
What could explain numbness like this?
Her presentation did not fit a typical L4-L5 disc-related pattern, and that mismatch is actually the useful clue. Radiculopathy from a disc bulge at this level usually comes with some combination of low back pain, pain radiating down the back of the leg, tingling, or a positive nerve tension sign — she had none of these.
Mild disc bulges are extremely common on MRI in adults over 40 and are frequently incidental rather than the source of symptoms.
Bilateral, symmetric numbness confined to the sole of the foot, without back pain or radicular signs, is more typical of:
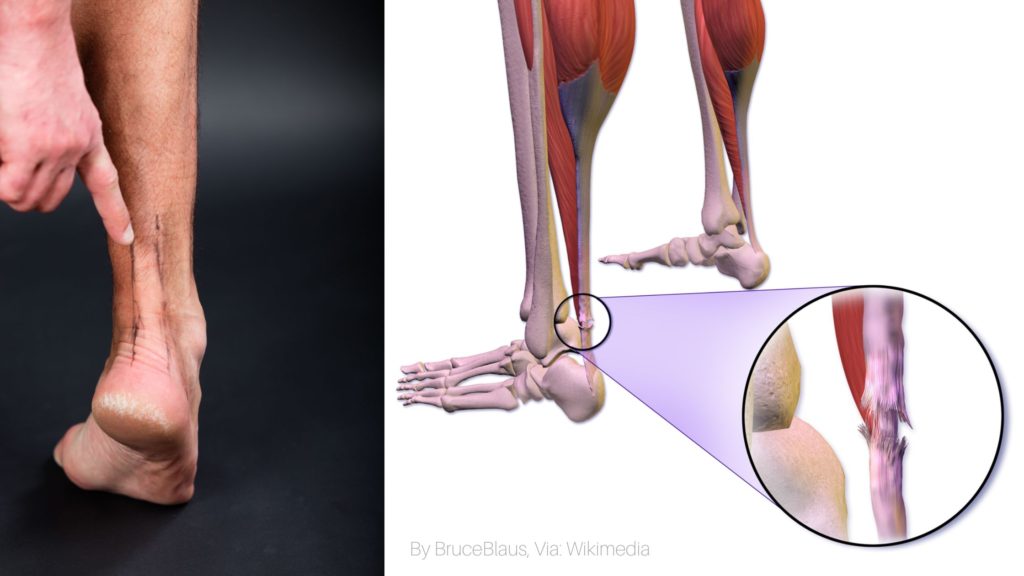
- Tarsal tunnel syndrome — compression of the posterior tibial nerve behind the inner ankle, which can cause sole numbness and weakness even when the low back is completely normal.
- Peripheral polyneuropathy — a length-dependent nerve problem, not always related to diabetes, that can also arise from vitamin B12 deficiency, thyroid dysfunction, alcohol use, or certain medications, and typically starts symmetrically in both feet.
- Small-fiber neuropathy — affects the fine sensory nerves responsible for light touch, and can present with normal reflexes and normal nerve conduction studies, which makes it easy to overlook.
In this case, her response to galvanic stimulation over the peripheral nerve pathway — rather than to lumbar traction or spinal extension exercises aimed at the disc — supports a peripheral rather than spinal cause.
What recent research says
- Tarsal tunnel syndrome has a low population prevalence (around 0.4–0.5%) and no single agreed-upon diagnostic test, which contributes to frequent underdiagnosis and diagnostic errors in routine practice.1
- A 2026 nerve-ultrasound study defined clinically confirmed tarsal tunnel syndrome as numbness confined strictly to the sole of the foot, sparing the top of the foot, with polyneuropathy specifically excluded on nerve conduction testing — a pattern that closely matches this case.2
- A systematic review covering over 4,000 tarsal tunnel patients found diabetes was the most frequently reported underlying cause, present in roughly 30% of cases — which is exactly why ruling out diabetes was an early priority in this patient’s assessment.3
- Even when nerve conduction studies are normal, routine electrodiagnostic testing only measures large-fiber function, so small-fiber nerve damage — a possible explanation when numbness persists without a clear structural cause — can be missed entirely.4
When bilateral foot numbness needs urgent attention
Most cases of foot numbness are not an emergency, but see a doctor promptly if the numbness:
- Comes on suddenly rather than gradually
- Is accompanied by weakness that keeps getting worse
- Spreads upward from the feet toward the knees
- Occurs together with loss of bladder or bowel control, or numbness in the saddle area (seek same-day evaluation)
- Occurs alongside unexplained weight loss, known diabetes, thyroid disease, or heavy alcohol use
Her presentation had none of these features and had been stable for years, which is why a conservative physiotherapy trial was a reasonable first step before further neurological workup.
Final word
This case is a reminder that an MRI finding and a patient’s actual symptoms don’t always line up — and when they don’t, it is worth treating what the patient is telling you rather than what the scan says. Her numbness responded to treatment aimed at the peripheral nerve, not the spine, which is a strong clue that the disc bulge was an incidental finding rather than the underlying cause.
If you are dealing with a similar pattern of foot numbness, our guide on common causes of sciatica can help you work out whether your symptoms point toward the spine or elsewhere. Have a similar case or a different insight? Drop a comment below.

The author is a physiotherapist who has been practising for the last 17 years. He holds a Bachelor's in Physiotherapy (BPT) from SVNIRTAR (Swami Vivekananda National Institute of Rehabilitation and Research), one of the prestigious physiotherapy schools in India.
Whatever he learns dealing with his patient, he shares it with the world through blogs and e-books. He also owns a YouTube channel, "Sunit Physiotherapist" with over 8 lakh active subscribers. Here, he shares everything he gets to learn serving the patient.